
 Revenue Cycle Management
 Medical Billing Services
 Medical Coding Services
 Specialty Medical Billing
 Healthcare Medical Billing
 Healthcare Medical Coding
 Insurance Verification
 Prior Authorization
 Appointment Scheduling
 Charge Entry
 Charge Review & Auditing
 Claims Submission
 Denials Management
 AR Follow-Up
 Payment Posting
 Patient Statements
 Reporting & Analytics
 Credentialing & Enrollment
 Compliance & Audit Readiness
 Clearing House & EDI Management
 Healthcare BPO
 Healthcare Back Office
 Full-Time Equivalent (FTE) Model


Mental health billing requires careful coordination across benefit verification, authorizations, time-based coding, documentation, claim submission and payer follow-up. Small gaps in any one of these steps can delay reimbursement or create avoidable denials.
ICS supports US mental health organizations with an India-based billing team for therapy, psychiatry, behavioral health and counseling workflows. Responsibilities, payer rules, exception queues and reporting are agreed before production so your team has clear operational visibility.
For integrated programs and broader behavioral-health workflows, review our behavioral health billing services.

Mental health billing can cover psychiatric evaluations, psychotherapy, medication-management visits, psychological testing, crisis services and telehealth workflows. Coverage and claim processing depend on the patient’s plan, applicable federal and state requirements, network status and payer policy. The billing team should verify the actual benefit path instead of assuming medical and behavioral-health benefits use the same administrator.
 selecting the right CPT codes for mental healthmatching them to correct ICD 10 codes for mental healthapplying modifiers and place of service rulessubmitting claims, following up, and managing denials
This work affects claim acceptance, payment posting, denials and AR follow-up. Repeated rejections, unresolved payer dependencies or documentation gaps can indicate that the organization needs defined queue ownership, quality review and escalation rules.

The workflow may include commonly used mental health procedure codes such as:
90791 — Psychiatric diagnostic evaluation90837 — Psychotherapy, 60 minutes90834 — Psychotherapy, 45 minutes90853 — Group psychotherapy90847 — Family psychotherapy with patient96130 — Psychological testing evaluation, first hour99213 — Office visit, established patientWe work with the full range of mental health CPT codes used across outpatient and inpatient settings, including:
CPT code for mental health evaluationCPT code for mental health counselingtherapy codes (individual, family, group)crisis services, partial hospitalization (PHP) and inpatient workflowsbilling for NP/psychiatric providers, including psychiatric nurse practitioner billing codestelemedicine billing, including CPT codes for mental health telemedicineCode selection should use the current code set, payer guidance and documentation applicable to the date of service. Unclear combinations should be routed for review rather than assumed.
Accurate diagnosis coding matters as much as procedure coding.
ICD 10 code for mental healthICD 10 mental health codesICD 10 diagnosis codes for mental healthICD-10 codes for mental health including commonly used categories for depression, anxiety, PTSD, substance-related, behavioral, and mood disordersscreening and administrative coding needs (including ICD 10 Z codes mental health when applicable)A controlled diagnosis reference can support consistency, but it should not replace the current ICD-10-CM code set, documented condition, medical necessity or payer guidance.
The agreed scope can extend beyond claim submission to eligibility, authorization, coding review, posting, denials and AR follow-up.
payer rules alignment and billing configurationdocumentation checklists so notes support billed servicessupport for EHR workflows, claim edits and billing handoffsclean claim preparationtimely claim submissionproactive follow-updenial categorization and resolutionappeals support for medical necessity and documentation gapsThese queues are tracked against the client’s baseline so changes in rejections, denials and aging can be reviewed with evidence.
Many practices need mental health billing and credentialing services together. We can coordinate payer enrollment support (or work alongside your credentialing team) so providers don’t lose weeks of billing time.
Mental Health billing is fraught with complexities that can lead to claim denials and revenue loss. Common challenges include:
Multiple behavioral health carve-out payers with separate billing portalsPrior authorization requirements for ongoing therapySession limit tracking and medical necessity documentationTelehealth billing for mental health servicesCredentialing with behavioral health networks
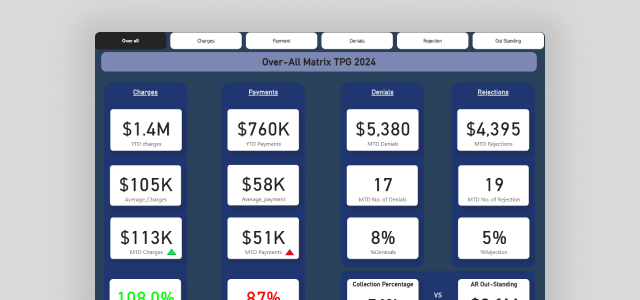
Mental health revenue-cycle management coordinates front-end verification, claim preparation, payment posting, denial work and AR follow-up across defined owners and queues.
eligibility and benefits verification workflowscharge capture review so sessions don’t go unbilleddenial trend tracking to prevent repeat issuesAR cleanup and structured follow-up schedulesreporting that makes sense to owners and managersThe operating review can track denial rate, days in AR, unresolved payer dependencies and queue ownership. Targets should be agreed from the organization’s baseline rather than assumed in advance.

ICS can support a defined billing function or a connected revenue-cycle workflow from India. Organizations can combine insurance eligibility verification with broader specialty billing services, or compare a dedicated FTE team with the percentage-based billing model.
Before launch, ICS and the client document access, responsibilities, escalation paths, reporting and working-hour overlap.
workflow scope and queue ownershipsystem access and security controlspayer-rule and documentation exceptionsquality review and escalation cadenceperformance reporting and review ownershipThis gives prospective clients a practical basis for comparing delivery models without relying on generic vendor claims.
ICS supports US mental health organizations remotely from its India delivery team. The service plan is based on the client’s payer mix, systems, operating hours, service locations and state-specific requirements.
confirm payer, plan and network requirementsdocument authorization and referral rulesalign service-location and telehealth claim fieldsroute state- or payer-specific exceptions for reviewreport aging, denial causes and unresolved dependenciesOrganizations can discuss their actual locations and payer rules during the workflow review so the scope reflects real operational requirements.
We support:

outpatient mental health clinics

behavioral health groups

psychiatrists and medication management providers

psychologists and therapists

psychiatric nurse practitioners

multi-location practices and growing networks
If you bill Medicare or Medicaid, we can also help with payer rule checks, documentation consistency, and denial prevention.
 accurate CPT and ICD-10 support (not guesswork)consistent follow-up and denial resolutionstrong reporting and accountabilityoffshore execution from India with U.S. billing disciplinescalable support for solo providers through large clinic networks
ICS mental health billing specialists can support carve-out payer workflows, prior-authorization tracking, session-limit controls and time-based coding review when these functions are included in the agreed scope. Payer-specific exceptions are documented and routed for client review instead of being assumed.
The India-based delivery model combines defined queue ownership, HIPAA-aligned access controls, transparent reporting and an optional dedicated FTE structure. The engagement begins with a review of payer mix, systems, workload and internal responsibilities.
For applicable Medicare workflows, review the current CMS Behavioral Health Integration Services booklet and the CMS Medicare telehealth services list. Payer and date-of-service rules still control each claim.

A workflow review maps payer requirements, authorization responsibilities, coding inputs, denial queues and reporting before the delivery model is finalized. This helps both teams understand what ICS owns, what remains with the client and how exceptions will be escalated.
These checkpoints summarize published CMS guidance for mental health claims. The payer’s policy and the rule in effect for the date of service always apply.
Medicare lists several eligible professionals for mental health services, including physicians, clinical psychologists, clinical social workers, nurse practitioners, physician assistants, marriage and family therapists and mental health counselors. Each type must meet its own qualification and coverage requirements.
Incident-to behavioral health services by auxiliary personnel are exempt from the direct supervision requirement. They can be furnished under general supervision, meaning the supervising physician or non-physician practitioner need not be present.
CMS does not define behavioral health services by a list of HCPCS codes. It generally treats them as services for the diagnosis, evaluation or treatment of a mental health disorder, including substance use disorders.
A partial hospitalization program is a structured, intensive outpatient psychiatric program. Medicare covers it in hospital outpatient departments and community mental health centers, and patients receive care less than 24 hours a day.
An intensive outpatient program is a distinct, organized ambulatory treatment service with less than 24-hour daily care, delivered outside the home or an inpatient or residential setting. It requires a physician certification and plan of care.
Behavioral health integration links behavioral health with primary care, and Medicare pays for BHI services over a calendar month. Psychiatric collaborative care is a specific type of BHI using a psychiatric consultant.
An India-based team can add defined billing capacity when access, responsibilities, coverage windows, quality review and reporting are agreed before production.

Significant Cost Reduction

Experienced Billing Support

Strong Security Measures

Defined Queues and Escalations

HIPAA-aligned access controls

Structured denial follow-up

Flexible US Working Windows

Who We Are?
ICS delivers India-based medical billing support for US healthcare organizations. The delivery model combines defined responsibilities, specialty-aware workflows, secure access and reporting aligned to the client’s operating needs.
Our approach to these challenges involves substantiated, budget-friendly strategies.

An India-based team can provide dedicated capacity and predictable queue ownership when scope, staffing assumptions and reporting cadence are clearly defined.
Quality checks can identify missing information, unsupported coding and payer-rule exceptions before submission. Recurring rejection and denial causes should be reported by queue and owner.
You will receive regular updates and substantiated account assistance. We ensure you stay
streamlined throughout each phase of the billing process.
We use documented review and exception workflows before submission, then monitor clearinghouse and payer responses through the agreed follow-up queues.
We can work within client-approved EHR, practice-management and clearinghouse systems when access, security controls and technical responsibilities are agreed during discovery.


Speak to our Experts on
End-to-End Medical Billing Services provider across entire US.

We offer medical billing services that feed to different types of medical practices.
 Ambulance
 Cardiology
 Radiology
 Family Practice
 Ophthalmology
Whether you operate as an individual practitioner or manage a healthcare association with multiple sites, we offer a solution tailored to your requirements.
With over a decade of experience serving diverse specialties and provider groups across the U.S., we ensure you get local-quality support, regardless of location.
 Support for US mental health organizations HIPAA-Compliant Offshore Billing Experts Specialized Teams for State-Specific Billing Needs
Select your location below to learn how we support practices like yours.
To ensure top-notch service delivery, we use premier industry platforms similar to










Also, we offer support for custom APIs and integrations with customer systems, streamlining data synchronization and billing operations.

Discuss payer mix, workload, denial inventory, systems and reporting needs with ICS. Compare a dedicated team with a percentage-based model and define responsibilities before transition.
MENTAL HEALTH BILLING RESOURCES
Use these focused guides to review outsourcing, insurance complexity and denial controls without duplicating the commercial service scope.
What are CPT codes for mental health billing?
Mental health CPT codes include evaluation codes, psychotherapy codes, crisis-related services, medication management workflows, and other behavioral health procedure codes. The correct CPT selection depends on documentation, time rules, provider type, and payer policy.
Which ICD-10 codes are used for mental health?
ICD-10-CM diagnosis codes depend on the documented condition and visit purpose. Unsupported or incomplete diagnosis detail can cause payer edits, record requests or denials, so the workflow reviews documentation and current payer requirements before submission.
How do you handle billing for multiple insurances in mental health?
When included in scope, the team coordinates primary and secondary benefits, including behavioral-health carve-outs, according to the applicable plan and payer rules.
How are teletherapy claims reviewed?
Teletherapy claims are reviewed against the current payer, date-of-service, provider-type, place-of-service, modifier and documentation rules. Exceptions are routed for confirmation before submission.
How do you manage session limit tracking?
When authorization tracking is included in scope, the team records approved visits, used sessions, remaining limits and renewal dependencies, then escalates approaching limits to the agreed client owner.
What information is needed for mental health telemedicine billing?
The billing review may require the payer and plan, date of service, provider type, patient and provider locations, documented modality, service, time where applicable, place of service and any payer-required modifier.
How do you measure denial and AR improvement?
ICS establishes a baseline for denials, aging and unresolved payer dependencies, then reports changes by queue and cause. Results depend on the starting inventory, payer mix, documentation and agreed scope.
Do you work with Medicare and Medicaid mental health billing?
ICS can support Medicare, Medicaid and commercial payer workflows included in the agreed scope when the required system and portal access is available. Payer-specific policies, authorization requirements and client responsibilities are documented during discovery.
Can we outsource mental health billing to India?
Yes. An India-based delivery model can provide additional billing capacity with documented system access, responsibilities, working-hour overlap, escalation paths and reporting.
Can you support multi-location mental health organizations?
Yes. The scope can include multiple US service locations, with payer- and state-specific exceptions, access responsibilities and location-level reporting documented before production.
What is the psychiatric collaborative care model?
CMS describes psychiatric collaborative care services as a specific type of behavioral health integration. It uses a psychiatric consultant to enhance primary care services.
Can therapists other than physicians bill behavioral health integration?
Yes. Clinical psychologists, clinical social workers, marriage and family therapists and mental health counselors can bill HCPCS code G0323 when they personally perform the monthly care integration services and those services are the focal point of integration.
How are partial hospitalization and other mental health services reported on one hospital claim?
When a hospital furnishes non-partial hospitalization mental health services to a partial hospitalization patient, all of those services are reported together on the same hospital claim with condition code 41.
Tell us your specialty, payer mix and billing priorities.
Build a dedicated offshore team or align billing fees with collections.

“ Partnering with ICS transformed our revenue cycle. Claim approvals are faster, denials have dropped significantly, and we finally have clear visibility into our billing performance. ”
Founder, Sunrise Family Clinic

“ The ICS team is knowledgeable, responsive, and deeply committed to helping our practice grow. Their customized dashboard gives us real-time insights we never had before. ”
Orthopedic Surgeon, CareAxis Hospital
“ We were drowning in paperwork and delays before ICS stepped in. Their team streamlined everything, from eligibility checks to patient billing, and gave us time to focus on care. ”
Practice Manager, Lotus Women's Health Center
“ ICS is more than a billing service—they’re a strategic partner. Their compliance-first approach gives us confidence, and their results speak for themselves. ”
Pulmonologist, Airway Specialty Clinic
“ With ICS, we saw a 35% increase in collections within the first quarter. Their billing accuracy and follow-up on aging claims are unmatched. ”
Dermatologist, ClearSkin Clinic
