
 Revenue Cycle Management
 Medical Billing Services
 Medical Coding Services
 Specialty Medical Billing
 Healthcare Medical Billing
 Healthcare Medical Coding
 Insurance Verification
 Prior Authorization
 Appointment Scheduling
 Charge Entry
 Charge Review & Auditing
 Claims Submission
 Denials Management
 AR Follow-Up
 Payment Posting
 Patient Statements
 Reporting & Analytics
 Credentialing & Enrollment
 Compliance & Audit Readiness
 Clearing House & EDI Management
 Healthcare BPO
 Healthcare Back Office
 Full-Time Equivalent (FTE) Model
Order and documentation intake
Define required order elements, medical-record access, prescriber follow-up, authorization responsibility and the point at which an item is ready for billing review.


DME billing begins before a claim is created. The supplier needs a connected record for the beneficiary, order, medical documentation, item, authorization when applicable, delivery, coding, payer requirements and service date.
ICS provides DME billing services for US durable medical equipment suppliers through an India-based delivery team. We support defined work queues or a connected revenue-cycle workflow with documented access, responsibilities, escalation paths and reporting.
Coverage and documentation requirements can differ by item, payer, beneficiary circumstances and date. A valid billing process should not assume that an earlier order, authorization or modifier applies to a new delivery. It should verify each claim against the current source record and applicable policy.
When information is incomplete, the claim should move to a traceable exception queue instead of being submitted with an unsupported assumption.
For Medicare claims, CMS states that a standard written order must be communicated to the supplier before claim submission, and certain items require a written order before delivery. Supporting medical-record information, correct coding and proof of delivery are also part of the general documentation framework.
Review the current CMS DMEPOS general documentation requirements for Medicare-specific guidance.


HCPCS codes and modifiers together determine how a DME claim processes, and an incorrect modifier can lead to rejection or denial. Modifier rules can change, so the team checks the current payer instruction for each claim. Read more in top modifiers used in DME billing.
Used for categories such as oxygen equipment, capped rental items, items needing substantial and frequent servicing, and inexpensive or routinely purchased items.
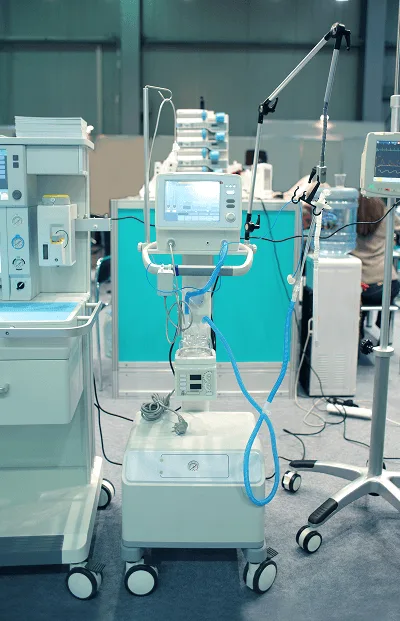
Durable medical equipment is therapeutic equipment prescribed by a licensed healthcare practitioner for certain medical conditions. Billing is supported only when the equipment is used for the prescribed condition and not for convenience. Examples include nebulizers, ventilators and kidney machines.
HCPCS codes and ICD-10 diagnosis codes work together: the HCPCS code identifies the item, and the diagnosis code identifies the medical condition it was prescribed for. See the end-to-end guide for DME billing services.
CMS maintains the DMEPOS fee schedule resources and updates files during the year. A listed amount does not replace coverage, documentation or payer-policy review.
CMS also publishes current DMEPOS order and face-to-face encounter requirements. The billing team should use the rule effective for the item and service date.
DME billing outsourcing controls
A useful outsourcing plan assigns ownership at each handoff instead of treating DME billing as one undifferentiated queue. Confirm the following controls before production work begins.
Define required order elements, medical-record access, prescriber follow-up, authorization responsibility and the point at which an item is ready for billing review.
Document who validates HCPCS codes, modifiers, units, rental-versus-purchase status, payer edits and exceptions requiring client approval.
Set rules for proof of delivery, refill requests, continued-need documentation and recurring claim timing based on the item, payer and service date.
Separate clearinghouse rejections from payer denials, assign corrected-claim and appeal routes, track timely-filing limits and report unresolved dependencies.
Use the DME order-to-payment workflow guide and the DME denial-prevention guide to prepare your discovery checklist.
Use our guide to outsourcing DME billing to compare scope, source-document access, handoffs and reporting. A dedicated offshore FTE billing team can provide named capacity for stable volumes and defined queues. A percentage-based medical billing model may fit a broader billing scope aligned with collections.
Compare item mix, payer mix, monthly volume, rental cycles, refill workload, systems, authorization volume, denial inventory and internal oversight before selecting a model.
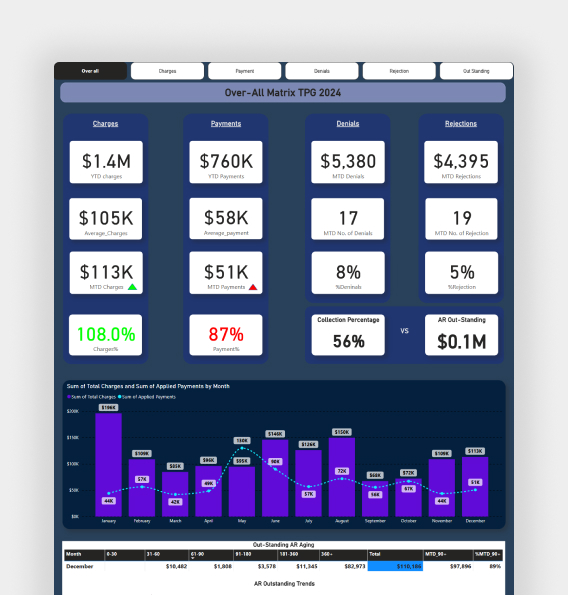
Tell us which items, payers, systems and queues you want reviewed. ICS can map order intake, documentation, delivery, claims, exception ownership and reporting before an engagement model is selected.
Explore all specialty medical billing services.
What is DME billing in medical billing?
It is the process of submitting claims for durable medical equipment using HCPCS, CPT, and ICD-10 codes, along with modifiers and documentation.
What codes are used for DME billing?
Most DME claims use HCPCS codes, supported by DME CPT codes when applicable, and appropriate ICD-10 diagnosis codes.
What is the difference between DME billing and regular medical billing?
DME billing requires stricter documentation, proof of delivery, equipment eligibility checks, and frequent modifier usage compared to standard professional billing.
Can DME be billed to commercial insurance?
Yes. DME billing applies to Medicare, Medicaid, commercial plans, workers’ comp, and private pay, each with different rules.
What are common DME billing errors?
Incorrect HCPCS codes, missing modifiers, incomplete documentation, wrong diagnosis linkage, and delayed submissions.
What is DME RCM?
DME revenue cycle management covers the full billing lifecycle from eligibility through payment posting and collections.
Is outsourcing DME billing safe?
Yes, when handled by a compliant offshore billing partner with HIPAA-aligned processes and payer experience.
Can ICS handle high-volume DME billing?
Yes. We support small suppliers and large multi-location DME operations.
What do the RR, NU and UE modifiers mean in DME billing?
RR indicates rental, NU indicates a new equipment purchase and UE indicates a used equipment purchase. They are used for categories such as oxygen equipment, capped rental items, items needing substantial and frequent servicing, and inexpensive or routinely purchased items.
What are the capped rental modifiers KH, KI and KJ?
With RR on capped rental items, KH indicates the initial claim and first-month rental, KI the second and third capped rental months, and KJ the fourth to thirteenth capped rental months. The team checks the current payer instruction for each claim.
Tell us your specialty, payer mix and billing priorities.
Build a dedicated offshore team or align billing fees with collections.

“ Partnering with ICS transformed our revenue cycle. Claim approvals are faster, denials have dropped significantly, and we finally have clear visibility into our billing performance. ”
Founder, Sunrise Family Clinic

“ The ICS team is knowledgeable, responsive, and deeply committed to helping our practice grow. Their customized dashboard gives us real-time insights we never had before. ”
Orthopedic Surgeon, CareAxis Hospital
“ We were drowning in paperwork and delays before ICS stepped in. Their team streamlined everything, from eligibility checks to patient billing, and gave us time to focus on care. ”
Practice Manager, Lotus Women's Health Center
“ ICS is more than a billing service—they’re a strategic partner. Their compliance-first approach gives us confidence, and their results speak for themselves. ”
Pulmonologist, Airway Specialty Clinic
“ With ICS, we saw a 35% increase in collections within the first quarter. Their billing accuracy and follow-up on aging claims are unmatched. ”
Dermatologist, ClearSkin Clinic
