
 Revenue Cycle Management
 Medical Billing Services
 Medical Coding Services
 Specialty Medical Billing
 Healthcare Medical Billing
 Healthcare Medical Coding
 Insurance Verification
 Prior Authorization
 Appointment Scheduling
 Charge Entry
 Charge Review & Auditing
 Claims Submission
 Denials Management
 AR Follow-Up
 Payment Posting
 Patient Statements
 Reporting & Analytics
 Credentialing & Enrollment
 Compliance & Audit Readiness
 Clearing House & EDI Management
 Healthcare BPO
 Healthcare Back Office
 Full-Time Equivalent (FTE) Model


Skilled nursing facility billing connects resident coverage, admission and stay information, assessment inputs, consolidated-billing responsibility, institutional claim data, remittances and follow-up. A missed handoff can affect more than one claim or service period.
ICS provides skilled nursing facility billing services for US facilities through an India-based delivery team. We support a defined queue or a connected SNF revenue-cycle workflow with documented responsibilities, access controls, escalation paths and reporting.

Billing responsibility can change with the resident’s coverage and stay status. Medicare Part A SNF services are paid under a prospective payment system, while consolidated-billing rules determine which services are included and which may be excluded. Other payers can apply different authorization, contract and claim requirements.
The workflow should identify the payer path and service period before claim creation, then keep eligibility, assessment, provider, ancillary and claim data tied to the same resident record.
Before a claim is built, confirm the resident’s payer, coverage period, authorization and stay status. For Medicare, determine whether the service falls within a covered Part A SNF stay or another billing context and apply the current consolidated-billing files and exclusions.
CMS explains that SNF consolidated billing generally assigns the SNF responsibility for the package of care during a covered Part A stay, subject to specified exclusions. Review the current CMS SNF consolidated billing resources.


Medicare replaced RUG-IV with the Patient-Driven Payment Model (PDPM) for covered Part A SNF stays on October 1, 2019. RUG data can still matter for historical claims, payer contracts and state Medicaid workflows, so the billing team verifies the rule that applies to the payer and the date of service.
In the RUG system, accurate Minimum Data Set (MDS) assessment data directly determined payment classification. Read more about RUG levels in SNF billing.
A step-by-step guide to UB-04 forms and EDI 837I in skilled nursing facility billing.
What RUG levels were, and why they can still matter for historical claims and Medicaid workflows.
The 2025 Medicare SNF rule explained for healthcare professionals.
CMS maintains the Skilled Nursing Facility Prospective Payment System page with current payment-policy resources. Because annual and quarterly updates can change applicable files, the billing team should use the rule and reference material effective for the service date.
For claim-format detail, use our UB-04 and EDI 837I SNF billing guide. For historical claims and payer programs that still use case-mix groupings, review RUG scores, PDPM and current SNF billing use.
A dedicated offshore FTE billing team can provide named capacity for stable volumes, defined work queues and direct operational ownership. A percentage-based medical billing model may fit a broader billing scope where fees are aligned with collections.
Compare census, payer mix, monthly claim volume, systems, ancillary coordination, denial inventory and internal oversight before selecting a model.
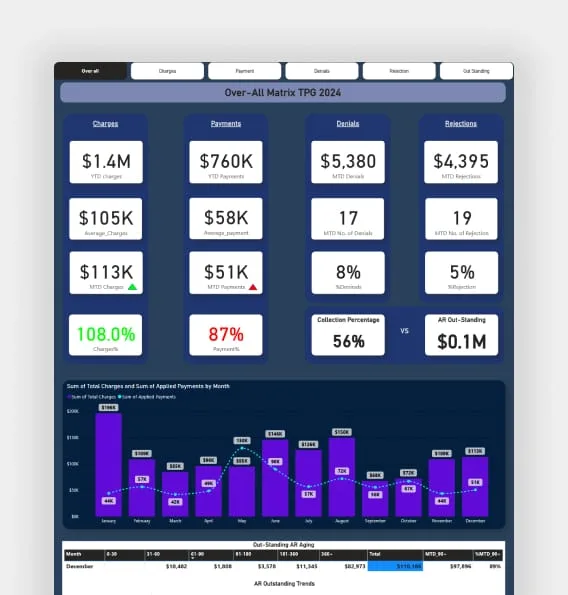
Tell us which facilities, payers, systems and queues you want reviewed. ICS can map inputs, claim handoffs, exception ownership and reporting before an engagement model is selected.
What is SNF consolidated billing?
SNF consolidated billing means most services for Medicare Part A residents are bundled into the facility’s payment and cannot be billed separately.
What services are excluded from SNF consolidated billing?
Certain services like specific chemotherapy drugs, ambulance transport, and select high-cost therapies may be excluded based on CMS lists.
How are SNF claims billed to Medicare?
SNF claims are billed using CPT codes, ICD-10 diagnosis codes, revenue codes, and HIPPS codes per Medicare guidelines.
Do you handle Medicare and Medicaid SNF billing?
Yes. We support both Medicare SNF billing and Medicaid skilled nursing facility billing.
Can SNF billing be outsourced to India?
Yes. Many U.S. facilities outsource SNF billing to India for cost efficiency and specialized expertise.
What causes denials in SNF billing?
Common causes include consolidated billing violations, incorrect coding, missing documentation, and revenue code mismatches.
Do you manage SNF discharge and transfer coding?
Yes. We handle CPT codes for SNF discharge, transfers, and follow-up care.
How do you help reduce AR days?
We focus on clean claims, proactive follow-up, denial resolution, and structured AR tracking.
Do you support multi-location SNF operators?
Yes. We support single facilities as well as multi-state SNF networks.
How long does SNF billing onboarding take?
Onboarding typically takes 2–4 weeks depending on system access, payer enrollment, and workflow complexity.
What replaced RUG levels in SNF billing?
Medicare replaced RUG-IV with the Patient-Driven Payment Model (PDPM) for covered Part A SNF stays on October 1, 2019.
Do RUG levels still matter for SNF billing?
RUG data can still matter for historical claims, payer contracts and state Medicaid workflows, so the team verifies the rule that applies to the payer and the date of service.
Tell us your specialty, payer mix and billing priorities.
Build a dedicated offshore team or align billing fees with collections.

“ Partnering with ICS transformed our revenue cycle. Claim approvals are faster, denials have dropped significantly, and we finally have clear visibility into our billing performance. ”
Founder, Sunrise Family Clinic

“ The ICS team is knowledgeable, responsive, and deeply committed to helping our practice grow. Their customized dashboard gives us real-time insights we never had before. ”
Orthopedic Surgeon, CareAxis Hospital
“ We were drowning in paperwork and delays before ICS stepped in. Their team streamlined everything, from eligibility checks to patient billing, and gave us time to focus on care. ”
Practice Manager, Lotus Women's Health Center
“ ICS is more than a billing service—they’re a strategic partner. Their compliance-first approach gives us confidence, and their results speak for themselves. ”
Pulmonologist, Airway Specialty Clinic
“ With ICS, we saw a 35% increase in collections within the first quarter. Their billing accuracy and follow-up on aging claims are unmatched. ”
Dermatologist, ClearSkin Clinic
