
 Revenue Cycle Management
 Medical Billing Services
 Medical Coding Services
 Specialty Medical Billing
 Healthcare Medical Billing
 Healthcare Medical Coding
 Insurance Verification
 Prior Authorization
 Appointment Scheduling
 Charge Entry
 Charge Review & Auditing
 Claims Submission
 Denials Management
 AR Follow-Up
 Payment Posting
 Patient Statements
 Reporting & Analytics
 Credentialing & Enrollment
 Compliance & Audit Readiness
 Clearing House & EDI Management
 Healthcare BPO
 Healthcare Back Office
 Full-Time Equivalent (FTE) Model


Behavioral health practices manage varied provider types, benefit structures, authorization rules, treatment documentation and in-person or telehealth encounters. A reliable billing workflow connects those inputs to the correct claim, remittance and follow-up queue.
ICS provides behavioral health billing services for US practices through an India-based delivery team. We can support a defined function or a connected revenue-cycle workflow, with access, responsibilities and escalation paths agreed before production begins.
For therapy, psychiatry, counseling and private-practice workflows, review our mental health billing services. For CCBHCs, nonprofit clinics and multi-location community programs, see our community behavioral health billing services.

Coverage may sit with a medical plan, a separate behavioral-health administrator or another network arrangement. Provider credentials, service location, authorization, documentation, time, modality and claim format can all affect processing.
The billing team should verify the applicable payer and plan first, then apply the current code set and payer guidance to the documented encounter. Unclear items should move to an exception queue instead of being guessed or written off.
The record should support the service reported, the provider who performed it, the date and modality, and any time or service components required by the applicable rule. Coding should use the current CPT, HCPCS and ICD-10-CM resources plus payer guidance for the date of service.
CMS publishes a current Behavioral Health Integration Services booklet describing service components and care-team roles for Medicare BHI services. Practices should also apply the payer and benefit rules relevant to each patient.

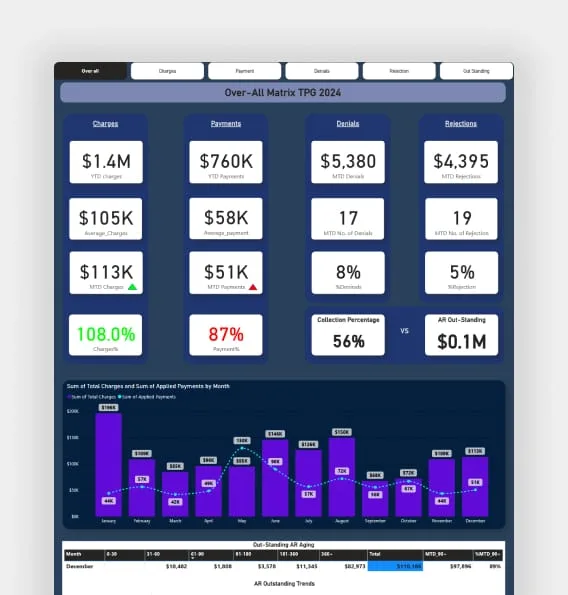
Behavioral health billing covers several practitioner types, and payer participation can differ by practitioner and location. Each provider has their own credentials, taxonomy and enrollment record, so the billing team reviews the rendering and billing provider, service location and payer enrollment before a claim is released.
For CCBHCs, nonprofit clinics and multi-location programs, see our community behavioral health billing services. For therapy, psychiatry, counseling and private-practice workflows, see our mental health billing services.
Payer enrollment is checked for each practitioner, location and service.
Psychotherapy claims depend on session length, so the record has to show precise start and end times. The code billed must match the documented session time. Missing times or the wrong time-based code can lead to denied claims, audits or lost revenue.
The team checks each note against the service billed and routes unclear items to an exception queue rather than guessing. Read the full breakdown in our guide to time-based CPT codes for behavioral health.
The behavioral-health benefit may follow a different network or administrator than the patient’s other medical benefits. The active plan, visit limits and referral or authorization requirements are confirmed and dated.
Authorization, referral and visit-limit details are recorded and tracked against the claim.
Unsigned notes, missing time and unclear service details receive standard exception reasons, which makes root-cause reporting useful.
Payer participation can differ by practitioner and location, so a credentialing issue gets its own owner instead of sitting in a general denial queue.
Requirements can change and may differ by payer, provider type, service, patient location and date, so they are reviewed separately.
Denials are routed by category (coverage, authorization, coding, documentation, credentialing or timely filing) rather than one generic queue.
Telehealth rules can differ by payer, provider type, service, patient location and date. The team should confirm the current eligible-service list, place-of-service and modifier guidance rather than applying a rule from a prior year. CMS maintains the current Medicare telehealth services list and related resources.
A telehealth edit should be routed with the claim date, payer, provider, patient location, service and submitted claim fields so the issue can be reviewed without rebuilding the case from memory.
A dedicated offshore FTE billing team can provide named capacity and direct ownership for stable volumes or defined queues. A percentage-based medical billing model may fit a broader billing scope where fees are aligned with collections.
Compare provider count, payer mix, monthly encounters, authorization workload, telehealth volume, denial inventory, systems and internal oversight before selecting a model.
Tell us which providers, payers, systems and queues you want reviewed. ICS can help map inputs, handoffs, exception ownership and reporting before an engagement model is selected.
For adjacent addiction-treatment workflows, review our Substance Abuse Disorder billing services.
Behavioral health billing resources
What is included in behavioral health billing services?
The scope can include eligibility and benefits, authorization tracking, credentialing support, coding review, claim submission, payment posting, denial follow-up and accounts receivable work. The exact systems, queues and escalation rules are agreed before transition.
How do you bill for behavioral health services?
The billing workflow should confirm the active payer path, provider and network status, authorization requirements, documented service, diagnosis support, location, modality and any time or modifier requirements for the date of service.
Can ICS support behavioral health telehealth billing?
Yes, when telehealth is included in the agreed scope. The team follows current client-approved payer guidance for eligible services, provider type, patient location, place of service and modifiers instead of applying a rule from a prior year.
Can an India-based team work in our behavioral health billing systems?
Yes. ICS can work within client-approved EHR, practice-management, clearinghouse and payer systems. Access controls, coverage windows, queue ownership and handoff responsibilities are documented during onboarding.
Can we outsource only behavioral health denials or aged AR?
Yes. An organization can start with a defined payer group, aging range or exception queue instead of transferring the full revenue cycle. Required notes, statuses and escalation criteria should be agreed before work begins.
How should we evaluate a behavioral health billing company?
Compare payer-path knowledge, specialty workflow experience, system compatibility, security controls, proposed roles, quality checks, queue ownership, reporting and transition planning. Request a defined scope and avoid unsupported collection, denial or turnaround guarantees.
Which CPT codes are used in behavioral health billing?
Individual psychotherapy is commonly billed with 90832, 90834 and 90837 according to session length. Family, group and crisis services use codes such as 90846, 90847, 90853, 90839 and 90840. The current CPT, HCPCS and ICD-10-CM resources and each payer’s policy apply for the date of service.
Why are behavioral health claims denied?
Common causes include missing session times, documentation that does not support the service billed, authorization or visit-limit issues, provider enrollment gaps and telehealth rule differences. ICS routes denials by category so the cause can be corrected and reported.
Do you bill telehealth behavioral health services?
Telehealth requirements can change and may differ by payer, provider type, service, patient location and date. The team checks the eligible-service list, place-of-service and modifier guidance that applies to each encounter.
What is the difference between behavioral health billing and community behavioral health billing?
This page covers behavioral health billing across provider types and telehealth workflows. Community behavioral health billing is for community mental health centers, CCBHCs, nonprofit clinics and multi-location programs, and has its own page.
Tell us your specialty, payer mix and billing priorities.
Build a dedicated offshore team or align billing fees with collections.

“ Partnering with ICS transformed our revenue cycle. Claim approvals are faster, denials have dropped significantly, and we finally have clear visibility into our billing performance. ”
Founder, Sunrise Family Clinic

“ The ICS team is knowledgeable, responsive, and deeply committed to helping our practice grow. Their customized dashboard gives us real-time insights we never had before. ”
Orthopedic Surgeon, CareAxis Hospital
“ We were drowning in paperwork and delays before ICS stepped in. Their team streamlined everything, from eligibility checks to patient billing, and gave us time to focus on care. ”
Practice Manager, Lotus Women's Health Center
“ ICS is more than a billing service—they’re a strategic partner. Their compliance-first approach gives us confidence, and their results speak for themselves. ”
Pulmonologist, Airway Specialty Clinic
“ With ICS, we saw a 35% increase in collections within the first quarter. Their billing accuracy and follow-up on aging claims are unmatched. ”
Dermatologist, ClearSkin Clinic
